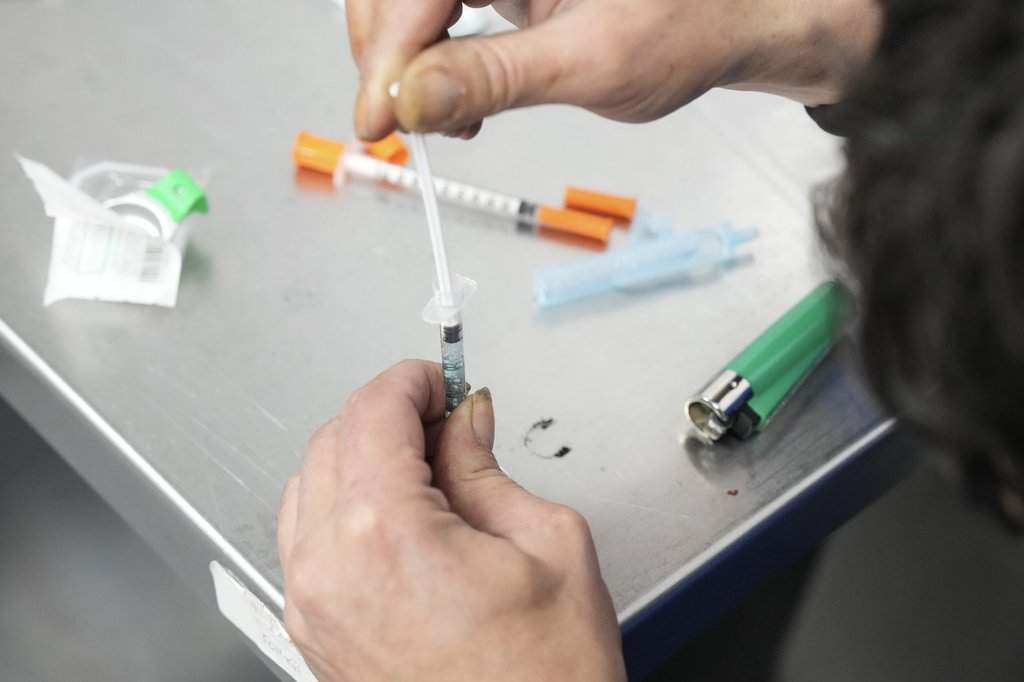
Regulatory intervention in clinical medicine operates on the assumption that rules alter behavior predictably. When the College of Physicians and Surgeons of Ontario approved amendments altering the prescription framework for safer supply opioids—mandating concurrent opioid agonist therapy, prohibiting take-home doses, and requiring monthly in-person assessments—the governance framework sought to mitigate black-market diversion. Yet, static compliance mandates in dynamic systems frequently generate unintended structural friction. Analyzing this regulatory shift requires moving past political rhetoric to evaluate the operational bottlenecks, incentives, and risk-migration pathways created when prescriptive rules collide with real-world clinical realities.
The Tripartite Mandate and Its Operational Mechanics
The regulatory alterations rest on three distinct operational requirements designed to tighten control over prescription-grade opioids such as hydromorphone. Each pillar attempts to eliminate a specific vector of risk, but each introduces severe logistical constraints into the health care delivery chain.
First, the requirement linking safer supply prescriptions exclusively to concurrent opioid agonist therapy, such as methadone or buprenorphine-naloxone, forces an intersection between two distinct clinical philosophies. Opioid agonist therapy aims at long-term stabilization and dose titration toward maintenance or withdrawal reduction. Safer supply, conversely, was designed as a harm reduction bridge to insulate users from the lethal toxicity of the illicit fentanyl market. Forcing patients onto opioid agonist therapy as a mandatory prerequisite assumes universal tolerability and psychological readiness, ignoring patients who experience adverse pharmacological reactions or psychological resistance to standard agonist protocols.
Second, the elimination of take-home doses through the explicit instruction of "no carries" transforms outpatient treatment into an on-site, observed administration model. This shifts the operational burden entirely onto community pharmacies and clinics. Patients must physically present themselves multiple times daily to ingest medication under supervision. This assumes an infrastructure of pharmacies with the physical space, staffing capacity, and security apparatus to manage high-volume, frequent-visitor populations—an assumption that fails in both under-resourced urban cores and rural districts lacking dense pharmacy networks.
Third, the mandate for monthly in-person clinical assessments codifies a strict monitoring frequency. While clinical oversight is a core tenet of responsible controlled substance management, rigid periodicity fails to account for patient stability or geographic isolation. In an environment characterized by a severe shortage of primary care physicians, imposing mandatory monthly face-to-face touchpoints risks creating administrative triage where physicians disengage from safer supply programs entirely to manage caseload limits.
The Cost Function of Divergent Incentives
Every regulatory architecture establishes an economic cost function for its subjects. When the cost of compliance exceeds the perceived benefit for either the clinician or the patient, system-level evasion or withdrawal occurs.
For clinicians, the liability and administrative overhead of supervising complex safer supply regimens under strict regulatory oversight alter the risk-reward calculation. Physicians operating solo or in overburdened community practices face a binary choice: absorb the operational friction of daily prescription management, or divest from treating patients with complex substance use disorders. The likely outcome is a contraction of the prescriber base, concentrating vulnerable patients into a smaller number of clinics and exacerbating regional service deserts.
For patients, the friction of "no carries" and daily observed dosing imposes a severe time and mobility tax. Individuals managing housing instability, employment, or chronic health conditions find frequent, rigid daily attendance logistically incompatible with stability. Rather than transitioning into mainstream care models, dislocated patients face abrupt discontinuation of pharmaceutical-grade alternatives. This creates an immediate supply vacuum. In an active market governed by inelastic demand, a vacuum in the regulated supply does not eliminate consumption; it redirects volume toward the illicit market, increasing reliance on unregulated street fentanyl and synthetic analogues contaminated with veterinary sedatives.
Systemic Feedback Loops and Risk Migration
The core failure of top-down regulatory tightening in public health is the phenomenon of risk migration. By targeting diversion at the point of distribution, regulators treat a symptom of systemic failure as a primary policy variable.
When take-home privileges are revoked, the intended output is a reduction in diverted prescription tablets reaching the secondary market. The secondary output, however, is the immediate destabilization of patients who relied on those carries to maintain employment or avoid street-level exposure. The resulting behavioral adaptation involves patients lingering around distribution pharmacies to manage frequent dosing intervals, or abandoning the formal medical system entirely.
Furthermore, the legal challenges mounted against these regulatory changes highlight the friction between administrative mandates and Charter-protected health securities. When regulatory bodies enact rules that patients and advocacy groups argue heighten the risk of overdose and mortality, the intervention transitions from a quality-assurance measure to a systemic shock. The legal pause on enforcement demonstrates that the judiciary recognizes the immediate operational dangers of abrupt policy shifts in fragile medical ecosystems.
Strategic Implementation Realities
Evaluating the trajectory of safer supply regulation requires acknowledging that neither absolute deregulation nor rigid restriction achieves optimal safety. A functional regulatory framework must balance diversion control with patient retention.
Future iterations of oversight cannot rely on blunt instruments like blanket bans on carries or mandatory universal protocols. Precision medicine demands risk-stratified policies where clinical discretion supersedes administrative uniformity. Regulators must incentivize inter-professional collaboration between primary care, addiction medicine, and pharmacy networks, ensuring that physical infrastructure matches operational demands before imposing attendance mandates. Without aligning regulatory rules with the ground-level capacity of the health care delivery network, attempts to engineer safety through restriction will continue to generate systemic instability.



