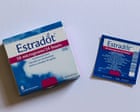
Your patch is not gone. Your brand is.
Every time a headline screams about UK HRT shortages, the playbook repeats itself like clockwork. A panic-inducing list of affected products gets rolled out. A few pharmacists and clinicians offer standard reassurance about switching to an equivalent option. Someone calls for a government taskforce to fix the supply chain. And millions of patients are left thinking they are locked in a zero-sum battle for a vanishing hormone.
That framing is lazy. Worse, it is misleading.
When you look closely at what is actually happening in UK menopause care—with nearly two million women aged 40 and over prescribed HRT in England in 2025-26 according to NHS Business Services Authority data—the real crisis is not an absolute disappearance of estradiol. It is brand rigidity, fragmented prescribing, and a pricing and manufacturing model that treats high-demand women's medicines like low-margin afterthoughts.
The Lazy Consensus Around "Product Shortages"
Standard coverage treats every supply hiccup as a simple equation: Brand X is out of stock, therefore patients cannot get their treatment.
Look at the actual mechanics. Estradot patches across strengths—25, 50, 75, and 100 micrograms—have faced recurring supply pressures and Serious Shortage Protocols (SSPs), such as SSP079 through SSP082 running into January 2027. FemSeven Conti patches have also been hit by DHSC medicine supply notifications (such as MSN/2026/048), while products like Progynova TS patches were discontinued rather than merely delayed.
Calling all of those the same thing blurs reality. A temporary bottleneck on one transdermal patch brand is not the same as a permanent discontinuation, nor is it the same as an absolute shortage of transdermal estradiol. Under SSPs for Estradot, community pharmacists can supply clinically equivalent alternatives like Evorel or Estraderm MX patches of the same strength one-for-one without forcing a patient back into a waiting room just for a brand name change. Meanwhile, British Menopause Society (BMS) equivalence guidance lays out how transdermal patches, gels like Oestrogel or Sandrena, and sprays map across doses when supplies tighten.
A brand shortage exposes a system built around rigid brand loyalty; a true clinical crisis happens when patients treat a brand name as the therapy itself.
I have watched supply chain teams and healthcare operators burn months chasing ghosts because they conflated SKU unavailability with therapeutic failure. When a specific brand hits a manufacturing snag or quota cap, panicked ordering spikes across adjacent SKUs, local wholesalers run dry first, and patients who only know their exact box design feel abandoned. The headline shouts "shortage," even when another transdermal option with the exact same active hormone is sitting one shelf over.
Why the Real Bottleneck Is Structural, Not Just Pharmaceutical
Department of Health and Social Care (DHSC) medicine supply disruption data shows that manufacturing issues—spanning capacity constraints, raw or packaging material hiccups, relocations, and supply chain delays—account for the majority of UK supply notifications, alongside regulatory, market, and demand factors. At the same time, global demand for menopause hormone therapy has surged while transdermal delivery systems remain notoriously unforgiving to manufacture at scale.
Transdermal patches and gels are not commodity tablets pressed out at billions-per-week speeds on generic lines. Adhesives, permeation enhancers, controlled release matrices, and pump or sachet packaging add layers of complexity. Add cross-border demand pressures—such as UK drugmakers fielding inquiries or talks around supplying estrogen patches into tight markets like the US—and you see why a single factory line hiccup ripples across clinics and pharmacies.
Imagine a scenario where ten thousand patients in one region are all prescribed one specific patch brand by name rather than by clinical need. When that single line slows down by 20%, ten thousand people hit the exact same bottleneck simultaneously—even if alternative patches or transdermal gels have unused headroom. Brand-locked prescribing turns a manageable supply ripple into a localized stampede.
Dismantling What People Actually Ask When Supplies Tight
"Which HRT products are affected right now?"
Asking for a static list of affected products is the wrong starting point because stock shifts week by week by strength, wholesaler allocation, and local pharmacy inventory. One strength of a patch can be tight while another moves normally. A high-street chain may be out while an independent pharmacy has stock on the shelf.
Instead of hunting for a master list and assuming you are out of luck, check whether your issue is a brand lock, a strength lock, or a route lock. If you need transdermal estradiol—especially relevant under NICE NG23 guidance for individuals with risk factors for venous thromboembolism—ask about clinically equivalent transdermal preparations rather than waiting passively for one specific box to reappear.
"Should I ration patches, cut them, or leave them on longer?"
No. Full stop.
Cutting patches that are not designed to be cut or leaving a patch on past its scheduled change window is a terrible work-around. Drug delivery rates across a patch matrix are engineered for specific surface areas and wear times; tampering with them ruins predictable absorption and can leave you under-treated or dealing with skin irritation.
Worse still, rationing by skipping doses or borrowing someone else's prescription turns a supply inconvenience into erratic hormone swings and avoidable safety risks. If you have an intact uterus and take estrogen, unopposed estrogen without adequate progestogen protection carries endometrial risks that you do not improvise around.
"What should I actually do if my usual HRT is hard to get?"
Drop the passivity and run a tighter playbook:
- Ask your pharmacist about active SSPs and immediate equivalents. If an SSP covers your product, you may be able to get an equivalent strength of an alternative patch directly through the pharmacy without a new GP appointment.
- Request brand-flexible or route-aligned options from your prescriber. If you tolerate multiple transdermal options or can transition safely between patch and gel/spray equivalents per BMS guidance, make sure your prescription gives you room to maneuver rather than dead-ending on a single SKU.
- Order earlier inside your prescription window. Last-minute requests collide with wholesaler cut-offs and weekend delivery gaps. Submitting requests with sensible lead time gives your pharmacy time to source across suppliers.
- Check independent and non-chain pharmacies. Allocation patterns differ across dispensing networks, and local stock pockets exist even during tight national notices.
- Keep progestogen aligned if you have a uterus. Never change your estrogen route or dose in isolation without checking how your progestogen regimen fits alongside it.
The Honest Downside of Switching and Flexibility
Being contrarian about brand loyalty does not mean switching is effortless or cost-free for every patient.
Skin sensitivity is real. Adhesive A might sit quietly on your skin for days while Adhesive B leaves a red, itchy outline. Absorption profiles can also feel subtly different from person to person even when two products share the same active hormone and nominal dose. For someone who finally dialed in symptom control after months of trial and error, being told "just switch" can feel dismissive—especially if a switch brings back night sweats, mood dips, or irregular bleeding while the body adjusts.
There is also administrative friction. Not every clinician has the same familiarity with equivalence tables, and patients who already fight to get timely menopause appointments should not have to do all the heavy lifting to keep their treatment steady.
Stop Chasing the Box. Fix the System Around It.
Supply chain taskforces and panicked roundups make great copy, but they will not refill a prescription on a Tuesday afternoon. Real resilience comes from understanding the difference between losing a brand and losing treatment, refusing dangerous DIY work-arounds, and demanding prescribing flexibility that matches how medicines are actually manufactured and dispensed.
Your body cares about steady, safe hormone delivery—not the logo on the foil wrapper.


